TREATING TN WITH SURGERY
QUICK FACTS
- Surgery may be considered when medicines do not control trigeminal neuralgia (TN) pain, cause unacceptable side effects, or when TN has a serious effect on everyday life.
- Before surgery, a clinician experienced in TN should confirm the diagnosis and review the relevant investigations, including MRI where appropriate. Patients should be able to discuss possible procedures with a neurosurgeon.
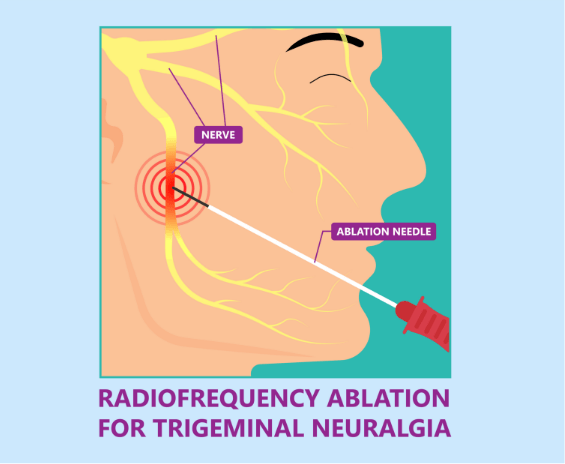
- Options may include microvascular decompression (MVD), percutaneous procedures such as radiofrequency treatment, balloon compression or glycerol injection, and stereotactic radiosurgery. The procedures have different aims, benefits and risks.
- Suitability depends on the type of TN, imaging findings, previous treatment, general health and the patient’s preferences. A procedure appropriate for one person may not be appropriate for another.
- Early discussion with a neurosurgeon is encouraged, but the best time to undergo surgery has not been established. No procedure can guarantee permanent pain relief.
HOW SUCCESSFUL IS SURGERY?
Published pain-relief results vary widely. Studies differ in the patients included, how pain relief is defined, whether medicines are still needed, and how long people are followed up. Percentages from different studies should not be treated as directly comparable success rates or a prediction of an individual’s outcome.
The Royal College of Surgeons of England’s guidelines for the management of trigeminal neuralgia (2021) summarise published surgical outcomes and their limitations. The NHS treatment information explains the main options and possible complications.
Ask your specialist about the likely chance of meaningful pain relief in your circumstances, the risk of recurrence, facial numbness and other complications, and what follow-up would be offered. Do not alter prescribed medication without advice from your clinical team.

MICROVASCULAR DECOMPRESSION (MVD)
PERCUTANEOUS PROCEDURES
RADIOFREQUENCY LESIONING
GLYCEROL INJECTION

BALLOON COMPRESSION
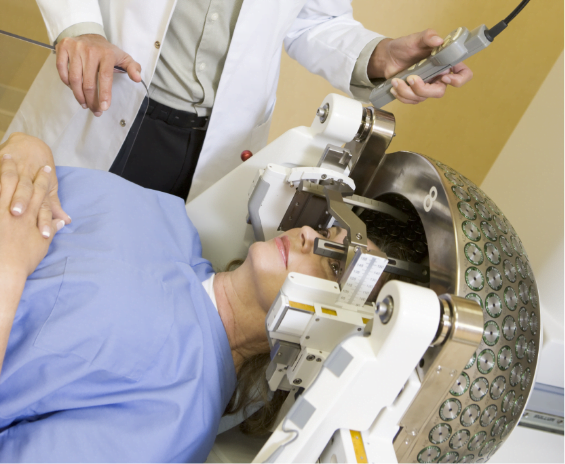
STEREOTACTIC RADIOSURGERY

YOUR QUESTIONS
HOW DO I CHOOSE A NEUROSURGICAL TEAM?
Ask about the team’s experience of diagnosing and treating TN, the procedures it offers, its audited outcomes and complication rates, and how your MRI findings influence its recommendation. It is reasonable to ask for a second opinion. There is no reliable universal minimum number of MVD operations per year that can, on its own, establish whether a surgeon is suitable.
MY PAIN IS NOT CLASSICAL TN – WOULD SURGERY HELP?
TN may be classified as classical, secondary or idiopathic. Some people also have continuous pain between attacks. Persistent trigeminal neuropathic pain following an injury and post-herpetic neuralgia are different diagnoses and do not automatically respond to the procedures used for TN. If TN is associated with multiple sclerosis, treatment must also be assessed individually. A specialist should confirm the diagnosis and explain which, if any, procedure is appropriate.
WILL SURGERY STOP MY PAIN?
Surgery can bring substantial relief for some people, but pain may persist or return. MVD may provide lasting relief in appropriately selected patients with neurovascular compression, but it is a major operation with potential complications. Procedures that affect the trigeminal nerve can cause facial numbness and, rarely, troublesome new pain. Pain relief after stereotactic radiosurgery is often delayed. Your specialist should explain the expected benefits, uncertainties and risks for your individual circumstances.
HOW CAN I FIND OUT MORE?
Read the Royal College of Surgeons of England guideline and the NHS treatment guide. TNA UK can also provide peer support and help you prepare questions for your clinical appointment. Experiences shared by other patients are valuable, but cannot predict your own outcome.